Published: 2021-05-23 · Updated: 2026-11-03
Toenail fungus (onychomycosis) is not a direct sign of diabetes, but fungal nail infections may occur more often in people with diabetes. High blood glucose, changes in immune defenses, peripheral neuropathy and circulation problems can complicate foot health. It is important to recognize symptoms, know when to seek medical advice and understand how to reduce the risk of complications.
Nail fungus often begins subtly with a small pale or yellow spot at the edge of a nail. Over time the nail may thicken, become brittle, change color or separate from the nail bed. With diabetes, potential skin injury and infectious complications also deserve attention.
No. Toenail fungus does not mean that a person has diabetes. Onychomycosis affects people of different ages, with or without diabetes. However, diabetes may increase susceptibility to fungal infections. Individual risk depends on age, glucose control, circulation and other health factors.
If you also experience excessive thirst, frequent urination, unexplained weight loss, fatigue or slow-healing wounds, speak with a clinician about blood glucose testing.
Persistently high blood glucose can affect immune defenses and make infections harder to control. Managing glucose is an important part of overall health and complication prevention.
Diabetes may also be associated with peripheral arterial disease. Reduced blood flow to the feet can impair oxygen delivery and slow wound healing.
Diabetic peripheral neuropathy can reduce sensation in the feet. Pressure from shoes, calluses or small injuries may go unnoticed. Nail fungus itself does not cause diabetic neuropathy.
Other risk factors include damp footwear, excessive sweating, walking barefoot in shared showers, sharing nail tools and a previous athlete's foot infection.
An early sign may be a white, yellow or brown spot near the edge of a nail. As infection progresses, the nail can thicken, become distorted, crumble, split or separate from its bed.
A thick nail may press on nearby skin and cause discomfort in shoes. Infection is not always painful, however. People with neuropathy may not feel even significant foot injuries.
Not every abnormal nail is infected with fungus: trauma, psoriasis and other conditions can look similar. Establishing the cause before treatment is important.
The main concern is not only the fungal infection but also secondary skin injury. A thick or distorted nail can press on nearby tissues, cause friction and create small wounds.
Broken skin may allow bacteria to enter. When neuropathy or impaired circulation is present, a wound may go unnoticed and heal slowly.
A diabetic foot ulcer generally develops through several interacting factors, including neuropathy, pressure, skin damage and circulation problems. Nail fungus is not its sole or direct cause, but nail changes may contribute to injury.
Appearance alone cannot always confirm onychomycosis. A clinician examines the nail and may take a sample for laboratory testing.
Tests may include microscopy, fungal culture or molecular analysis. Confirming the diagnosis is particularly important before prescribing oral antifungal medication.
Treatment depends on the number of affected nails, severity, other medical conditions and current medicines. Mild infections may be managed with nail-specific antifungal lacquers or solutions.
Ordinary antifungal skin creams may not penetrate the nail plate adequately and are not always appropriate for nail infections.
More extensive infection may require prescription oral antifungals such as terbinafine. Drug interactions, liver health and contraindications must be assessed before treatment.
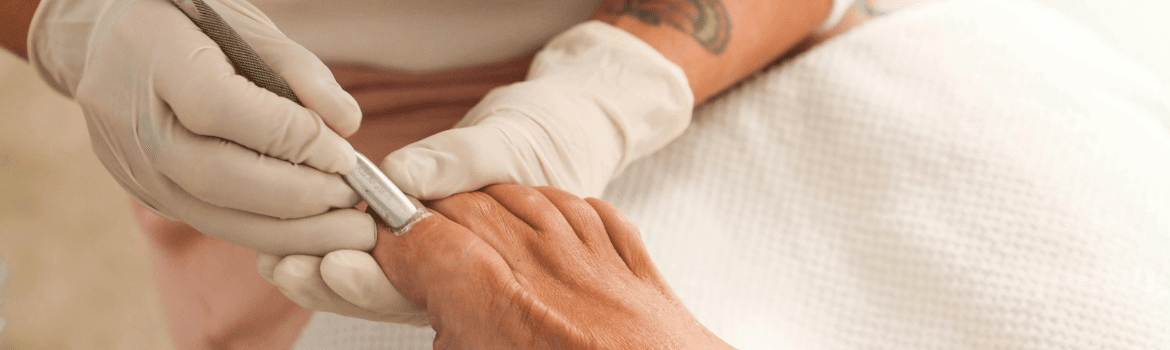
Very thick nails may need professional care. People with neuropathy or poor circulation should not attempt aggressive nail removal themselves.
Even after successful treatment, a healthy toenail may take 12–18 months or longer to grow out. Nail regrowth time is not the same as the duration of medication.
Vinegar, baking soda, essential oils and disinfectants are often promoted online, but evidence is insufficient for them to replace established antifungal treatment.
Harsh or concentrated substances may irritate or injure the skin. Such injuries can be especially problematic in diabetes, so discuss treatment with a qualified healthcare professional.
Related skin care products: EUBOS Diabetic Foot & Leg, 100 ml and EUBOS Dry Skin Urea 10% foot cream, 100 ml can moisturize dry skin, but do not treat nail fungus. Avoid open wounds and between-toe application unless advised by a clinician.
Inspect the soles, heels, spaces between toes and nails every day. Use a mirror or ask for help if you cannot see the underside of your feet.
Wash with lukewarm, not hot, water. Dry gently, especially between toes. Prolonged soaking is not recommended, particularly with neuropathy or skin injury.
Moisturize dry skin appropriately but keep the spaces between toes dry. Wear comfortable, well-fitting shoes and check inside them before putting them on.
Do not cut nails too short or dig deeply into corners. Seek professional care if nails are very thick, ingrown or sensation is reduced.
Foot hygiene: CUTASEPT Feet spray, 250 ml is a hygiene and prevention product, not a treatment for nail fungus. It contains alcohol; ask a clinician before use on sensitive or damaged skin.
Foot hygiene products can help maintain cleanliness, while skincare products support skin comfort. Disinfectants must be used only as directed by the manufacturer.
Antimicrobial activity does not automatically mean a product treats nail fungus. Antifungal medicines and ordinary hygiene products are not interchangeable.
If you have diabetes and notice new nail changes, consult a clinician, particularly if you have neuropathy, poor circulation or a history of foot ulcers.
A new wound or ulcer, spreading redness, swelling, pus, blackened skin, fever or significant deterioration requires urgent medical assessment. Lack of pain does not mean an infection is harmless.
Nail fungus is not a specific diabetes symptom. Discuss recurrent infections and other possible diabetes symptoms with a clinician.
High glucose, changes in immune defenses and other individual factors may contribute.
A thick or distorted nail may injure skin, but ulcers usually involve multiple risk factors.
Yes. Fungi can spread via contaminated surfaces, footwear and nail tools.
With diabetes, confirm the diagnosis and discuss treatment with a professional first.
Ordinary skin creams often do not penetrate the nail adequately.
Usually about 12–18 months, sometimes longer.
Keep feet dry, change socks, care for shoes and promptly treat athlete's foot.
This information is educational and does not replace medical advice.
Originally published: 2021-05-23 · Updated: 2026-11-03